

Key Takeaways
- Taking D3 with K2 has no established medical requirement, and no proven universal D3-to-K2 ratio exists, so ignore label claims about the "perfect" ratio.
- K2 can strongly interact with warfarin and other blood thinners; never start, stop, or change K2 without coordinating with your anticoagulation clinician.
- The adult upper limit for vitamin D is 4,000 IU per day from all sources; a combined K2 product does not reduce the risk of hypercalcemia from excess D3.
- Evidence that K2 prevents arterial calcification or heart disease is insufficient; proven heart protection comes from blood pressure control, cholesterol management, and lifestyle habits.
- The most promising bone data comes from a trial of MK-7 in postmenopausal women, so discuss bone loss risk with a clinician before assuming benefit for all adults.
- Get a baseline check of vitamin D, calcium, and kidney function, and bring every supplement bottle to your visits to avoid guesswork and interactions.
Vitamin K2 and vitamin D3 have become one of the most popular supplement pairings in 2026. Walk down any wellness aisle and you will see bottles promising stronger bones, healthier arteries, and better calcium balance. But the marketing often runs ahead of the science.
Many people buy a k2 vitamin with d3 product without asking basic questions. Do they need it? Is the dose right? Is it safe with their medicines? Those gaps lead to wasted money and, in some cases, real health risks.
This guide walks through the five most common mistakes. It explains what research supports, what it does not, and how a primary care team can help you decide. If you live in the Tampa Bay area, a visit to primary care is the safest place to start.
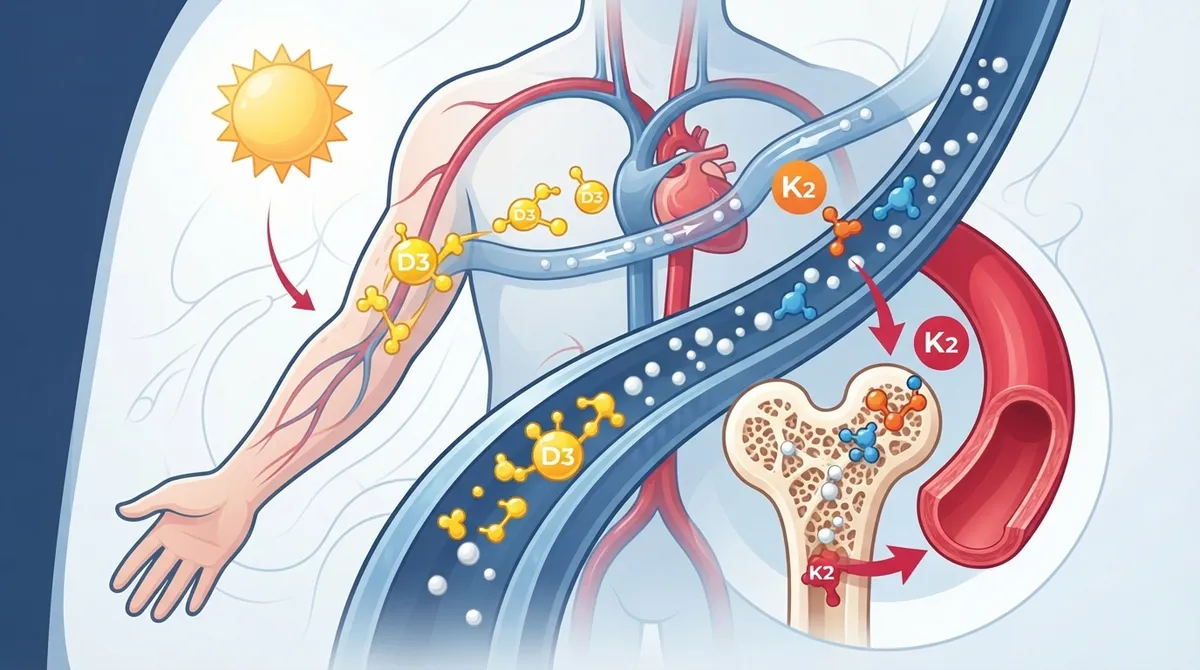
How Vitamin D3 and K2 Work Together
Vitamin D3 (cholecalciferol) helps your body absorb calcium. It also supports bone mineralization. Vitamin K2 (menaquinones, including MK-4 and MK-7) helps activate proteins involved in bone metabolism and in how the body handles calcium in tissues.
This is the basis for pairing them. The idea is simple: D3 helps calcium get in, and K2 helps calcium go where it belongs. That reasoning is sound in biology. However, a good theory does not prove better results for every person.
Here is a quick summary of each nutrient:
|
Nutrient |
Main Role |
Common Sources |
U.S. Intake Guidance (Adults) |
|---|---|---|---|
|
Vitamin D3 |
Supports calcium absorption and bone mineralization |
Sunlight, fatty fish, fortified foods, supplements |
RDA of 600 IU (15 mcg) through age 70; 800 IU (20 mcg) after age 70 |
|
Vitamin K (including K2) |
Helps activate proteins tied to bone and calcium regulation |
Fermented foods, some animal products, leafy greens (K1) |
Adequate intake of 90 mcg (women) and 120 mcg (men) for vitamin K overall |
Notice that the vitamin K numbers cover vitamin K as a whole. They are not a specific K2 target. That detail matters for the first mistake below.

Mistake 1: Assuming Everyone Who Takes D3 Needs K2
This is the most common error. Many labels imply that D3 is unsafe or incomplete without K2. That claim goes beyond the evidence.
There is no established medical requirement to pair vitamin D3 with K2. There is also no proven, universal ratio of D3 to K2. Claims that K2 reliably sends all calcium into bones are too strong. So are claims that K2 prevents artery calcification from vitamin D supplements.
Many people get enough vitamin K from food. Leafy greens supply vitamin K1. Fermented foods and some animal foods supply K2. If you eat a varied diet, you may not need a second pill.
A better first step is to ask why you are taking D3 at all. Some people take it because a blood test showed a low level. Others take it just because a friend did. Your reason should drive the plan.
Mistake 2: Expecting It to Prevent Heart Disease
Many ads suggest that a k2 vitamin with d3 supplement keeps arteries clear. The research does not support that claim yet.
A 2023 systematic review looked at 14 randomized trials of vitamin K supplementation. It found consistent effects on a blood marker called dp-ucMGP. But it found limited evidence for real vascular outcomes. A change in a lab marker or in arterial stiffness is not the same as fewer heart attacks, strokes, or deaths.
Evidence that K2, alone or with D3, prevents cardiovascular events is insufficient and inconsistent. If heart health is your goal, the proven tools are different:
- Blood pressure control and regular monitoring
- Cholesterol and blood sugar management
- Not smoking and staying active
- Weight management when needed
- Taking prescribed medicines as directed
Our team shares practical steps in 12 proven strategies for blood pressure management in 2026. These habits have far stronger evidence than any supplement pairing.
Mistake 3: Ignoring Blood Thinner Interactions
This mistake carries the highest risk. Vitamin K can strongly interact with warfarin and similar vitamin K antagonist anticoagulants. These medicines work by blocking the effects of vitamin K. Adding a K2 supplement can weaken them and raise clot risk.
If you take warfarin, follow these steps:
- Do not start a K2 supplement without talking to your anticoagulation clinician first.
- Do not stop one suddenly if you already take it.
- Keep your intake of vitamin K-rich foods steady from week to week.
- Ask whether your INR testing schedule needs to change.
- Bring every supplement bottle to your medical visits.
Consistency is the key idea. Your clinician can adjust your medicine dose around a steady intake. Sudden swings are what cause trouble.
Good prescription management includes supplements, not just pills from the pharmacy. Tell your care team about everything you take.
Mistake 4: Taking Too Much Vitamin D3
Some people assume that a combined product makes high doses safe. It does not. K2 does not remove the risks of too much vitamin D.
The adult tolerable upper intake level for vitamin D is 4,000 IU (100 mcg) per day from all sources. That includes food, supplements, and multivitamins. Higher doses are sometimes used for specific medical reasons, but only under professional supervision.
Too much vitamin D can cause hypercalcemia, which means high calcium in the blood. Possible effects include nausea, weakness, frequent urination, and kidney problems. People with kidney disease or a history of high calcium need extra care. Some medicines also raise calcium levels.
Watch for these common ways people overshoot:
- Taking a stand-alone D3 pill plus a multivitamin plus a combo product
- Using "mega-dose" products without a lab-confirmed need
- Combining supplements with fortified foods and not counting them
Add up your total daily intake. If the number looks high, ask your clinician before continuing.
Mistake 5: Skipping Testing and Medical Guidance
Guessing is the most expensive way to supplement. Without a baseline, you cannot tell if a product helped, did nothing, or caused harm.
A clinician may check your vitamin D level, calcium, kidney function, and other markers. This depends on your age, symptoms, medicines, and risk factors. Testing is not always needed for everyone. But it is often useful if you plan long-term, higher-dose use.
A primary care visit can also look at the bigger picture of bone health. That includes diet, activity, hormones, family history, and bone density screening when appropriate. Many people do not realize how much a routine annual physical exam can reveal about nutrient gaps and risk factors.
For people who want a more personalized view, DNA gene testing can offer added insight into health predispositions. It does not replace labs, but it can help guide a wider prevention plan.
What the Research Actually Shows for Bones
Bone health is where the evidence looks most promising, so it deserves a fair summary. A three-year randomized trial studied 244 postmenopausal women. They took MK-7 at 180 mcg per day. Compared with placebo, they showed slower declines in some bone density and bone strength measures (Knapen et al., 2013).
That is encouraging. But it does not prove the same benefit for all adults. The study group was specific. The product was MK-7 alone, not every D3 and K2 combination on the shelf. Results from one group do not automatically apply to younger adults, men, or people with other health conditions.
The honest summary looks like this:
|
Claim |
Evidence Level |
What It Means for You |
|---|---|---|
|
K2 may slow some bone loss in postmenopausal women |
Promising but mixed and population-specific |
Worth discussing if you are at risk for bone loss |
|
D3 and K2 prevent arterial calcification |
Insufficient and inconsistent |
Do not rely on it for heart protection |
|
A specific D3-to-K2 ratio is best |
No established ratio |
Ignore ratio claims on labels |
|
K2 improves lab markers like dp-ucMGP |
Consistent in trials |
A marker change is not the same as better outcomes |
Who May Want to Discuss D3 and K2 With a Clinician
Some groups have a stronger reason to look into these nutrients. They are not guaranteed to benefit, but a conversation is worthwhile:
- Postmenopausal women concerned about bone loss
- Adults over 70 who may need more vitamin D
- People with limited sun exposure or low dietary intake
- Anyone with a confirmed low vitamin D level
- People with conditions that affect nutrient absorption
Women in their 20s and 30s often have no primary care relationship. Yet this is the stage when bone density is built. A strong baseline matters. A routine annual wellness visit is a smart way to start.
Busy parents face a different problem. Time is short, and supplement shelves are confusing. A single visit that covers screenings, nutrition, and medicine review saves effort. Our guide on family primary care explains how this works for the whole household.
How to Choose a Supplement If Your Clinician Agrees
If your care team says a combined product makes sense, use a simple checklist:
- Check the D3 dose. Make sure the total from all sources stays within safe limits.
- Check the K2 form. Labels list MK-4 or MK-7. Ask which fits your plan.
- Look for third-party testing. This helps confirm the label matches the contents.
- Skip extreme claims. Avoid promises about "clearing arteries" or "perfect calcium balance."
- Review your medicines. Share the product with your clinician or pharmacist.
- Plan a follow-up. Decide when you will recheck labs or reassess the need.
Also remember that food comes first. Sunlight, fatty fish, eggs, fortified foods, and a varied diet all contribute. Supplements fill gaps. They do not replace healthy eating.
Why Personalized Primary Care Beats Guesswork
Supplement decisions work best when they fit your whole health picture. That is where a coordinated primary care team shines. At InCare, clinicians combine medical expertise with modern tools to build plans around you, not around a bottle label.
InCare serves patients in Tampa and Riverview, with convenient locations and virtual options. Our providers can review your labs, medicines, and goals. They can also offer related services such as IV hydration and vitamin drips and body composition analysis for patients who want a deeper view of their health.
Patients often tell us what matters most is feeling heard. You can see what our InCare patients say on Google to learn what the experience is like. You can also follow clinic updates on Instagram, Facebook, and TikTok.
Conclusion: Make a Smarter Choice With Your Care Team
A k2 vitamin with d3 supplement is not a magic fix. The science behind the pairing is reasonable, and bone data in some groups looks promising. But there is no universal need, no proven ratio, and no solid proof that it prevents heart disease. It can also interact with blood thinners, and extra vitamin D carries real risks.
Avoid the five mistakes: assuming everyone needs it, expecting heart protection, ignoring blood thinner interactions, overdoing vitamin D, and skipping medical guidance. When you do, you save money and protect your health.
Ready for advice built around your labs, medicines, and goals? Book your appointment with InCare today, or contact our team with questions. Bring your supplement bottles, and we will help you decide what truly belongs in your routine.
FAQs
Q: Should I take vitamin K2 with vitamin D3?
A: There is no established medical requirement to take them together. The pairing makes sense in biology, but it has not been proven to help everyone. Ask your primary care clinician based on your diet, labs, medicines, and bone health risks.
Q: Is there a recommended ratio of vitamin K2 to vitamin D3?
A: No evidence-based universal ratio exists. Product labels that promote a "perfect" ratio go beyond what research has shown. Focus on a safe total vitamin D intake and a plan set by your clinician.
Q: Can I take vitamin K2 if I use warfarin or another blood thinner?
A: Only with guidance from your anticoagulation clinician. Vitamin K can substantially interact with warfarin and similar medicines. Do not start, stop, or change K2 or vitamin K-rich foods without coordinating your care.
Q: What are the risks of taking too much vitamin D3?
A: Too much vitamin D can cause hypercalcemia, which may lead to nausea, weakness, and kidney problems. The adult upper limit is 4,000 IU (100 mcg) daily from all sources, unless a clinician directs a higher dose. A combined K2 product does not remove this risk.
Q: Can vitamin K2 prevent calcium from building up in arteries?
A: Current evidence is insufficient and inconsistent. Trials show effects on lab markers, but not clear reductions in heart attacks, strokes, or deaths. Proven heart protection comes from blood pressure, cholesterol, and lifestyle care.


